Tag: patient safety

What is a Smart Room? How it works and why it matters now

smart room image with technology

What is a Smart Room? 

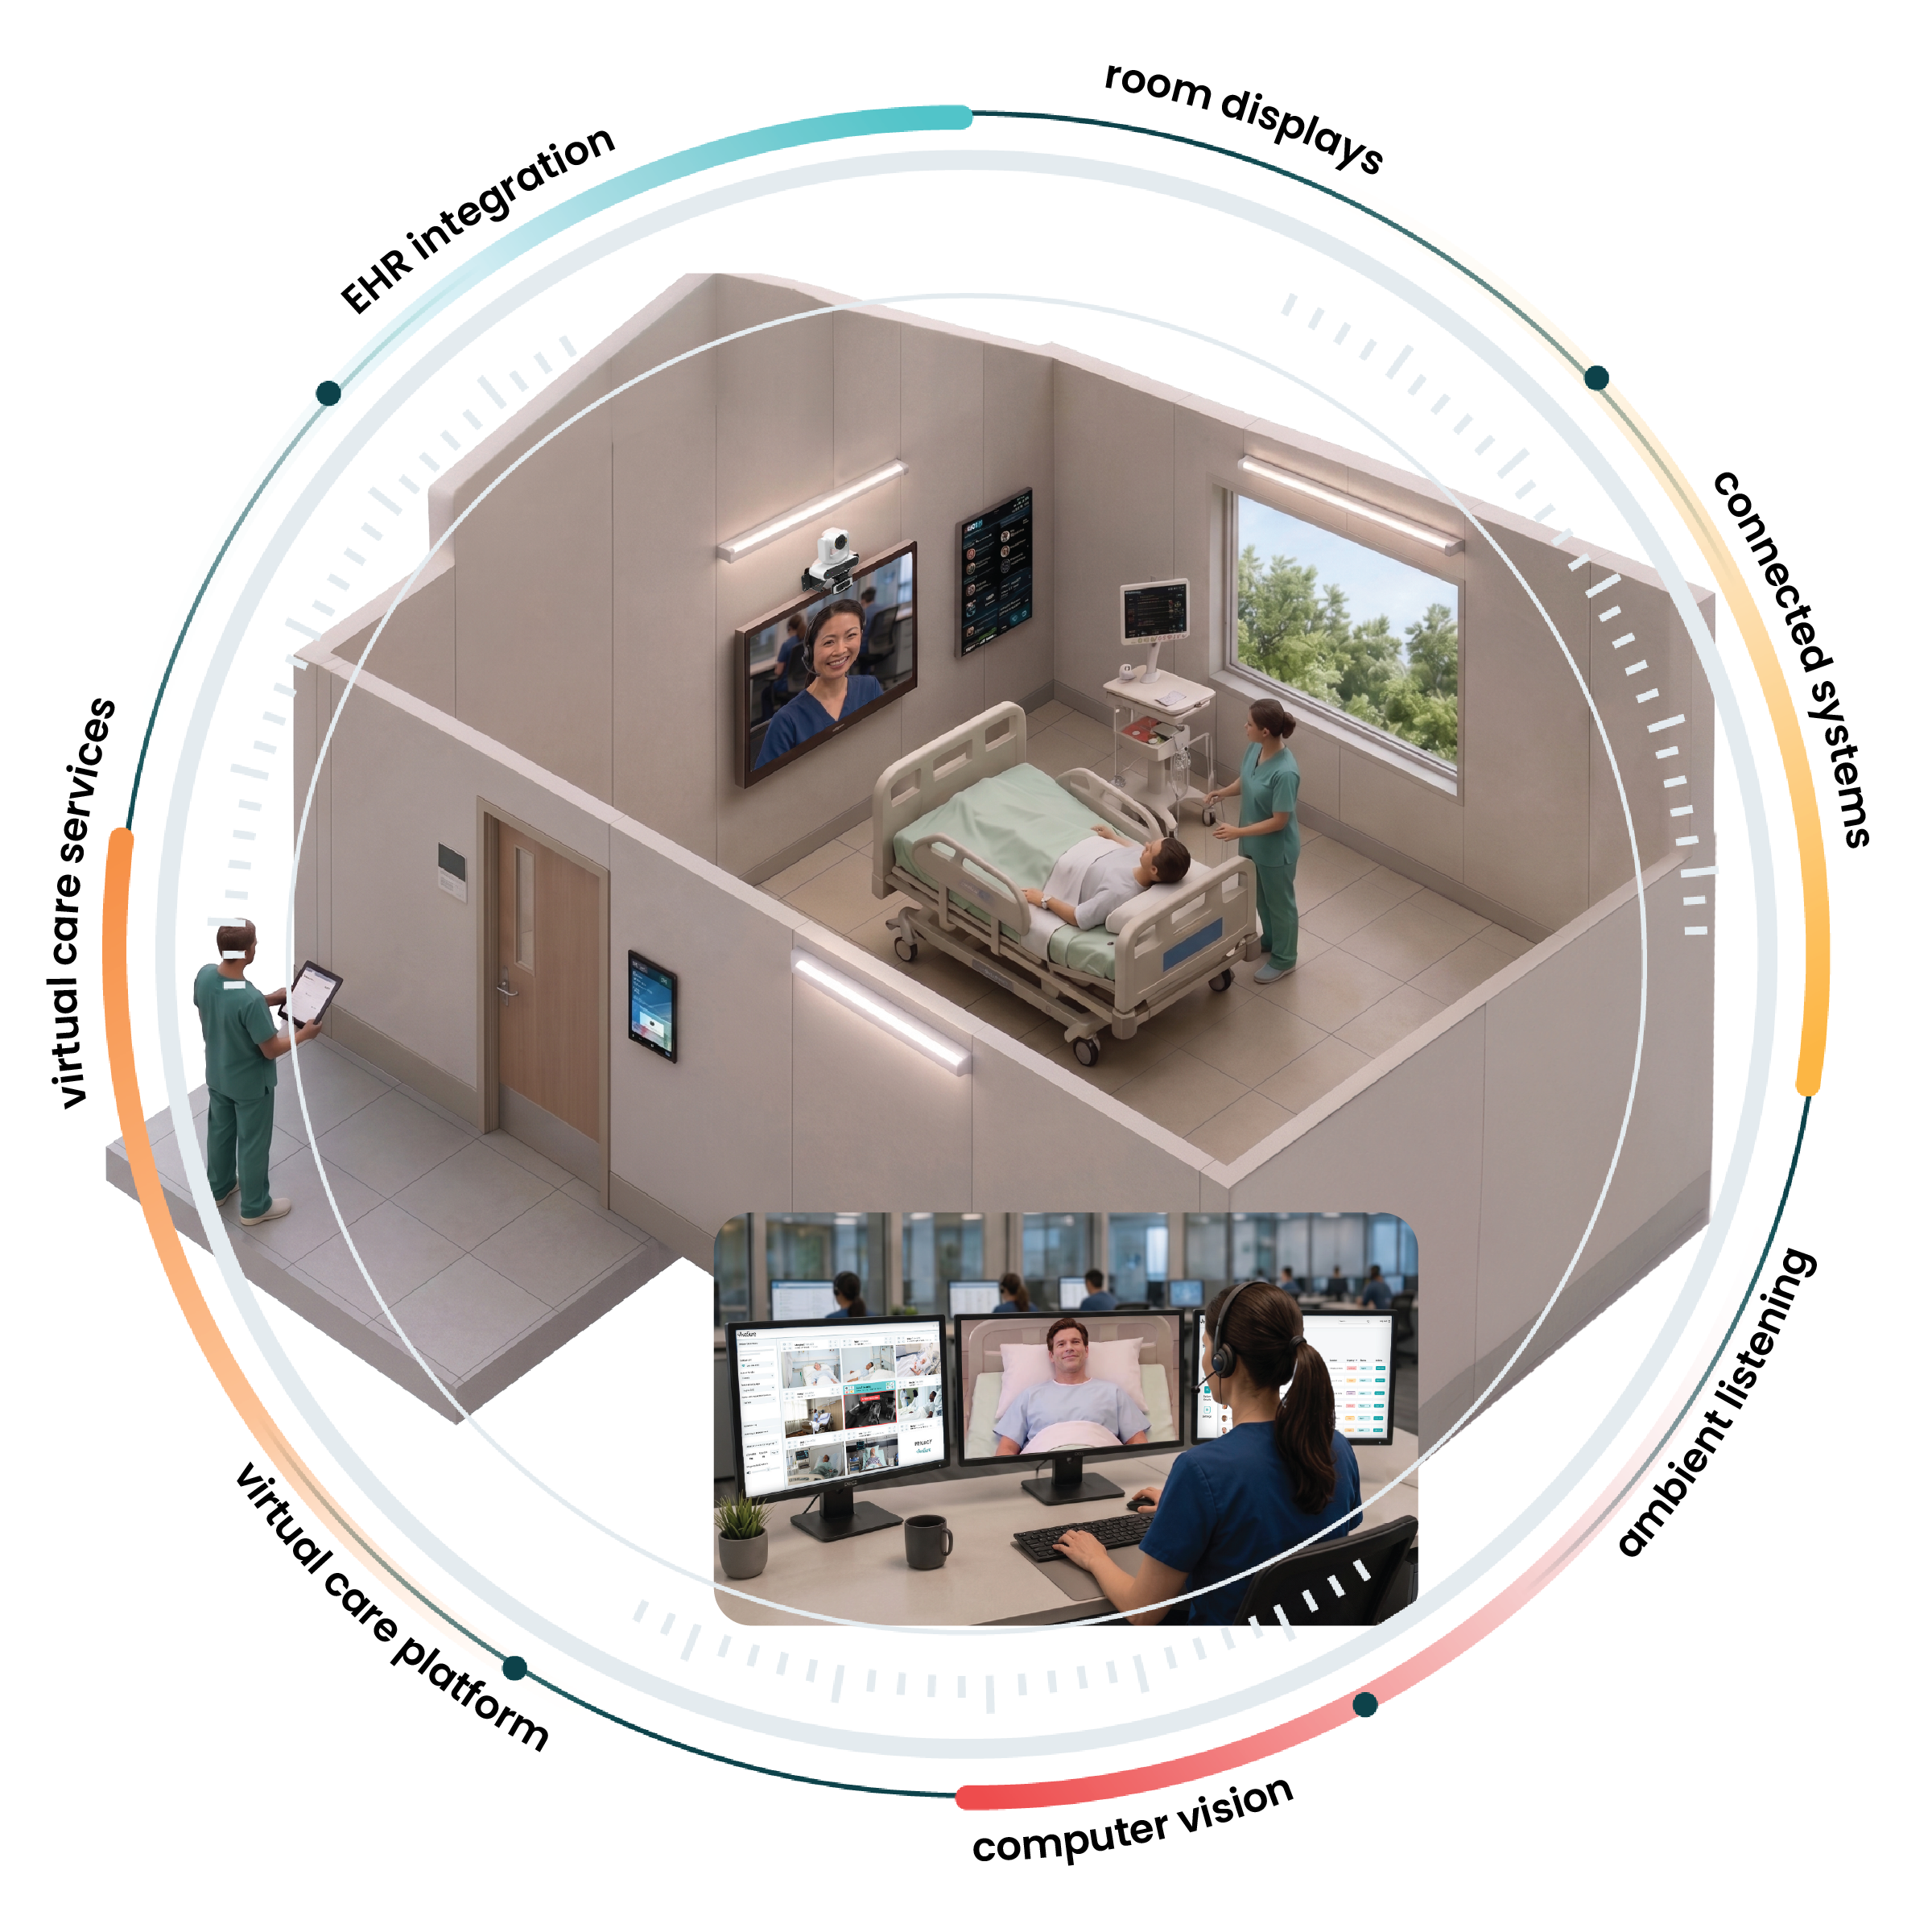
A smart room is a connected care environment where technology, workflows, and AI work together to support patients, caregivers, and hospital operations. It combines virtual care, ambient listening, computer vision, digital whiteboards, patient engagement, and digital door signs, all connected to the systems hospitals already rely on: the EHR, nurse call, translation services, and clinical peripherals. 
Building a smart room starts with a strategy

The first step in building a smart room is defining the strategy behind it. No two smart rooms look the same, because each health system should build its strategy around its own gaps and priorities. For one hospital, the most pressing gap might be falls and pressure injuries on high-risk units, or the cost of 1:1 sitters. For another, it might be nurses losing hours to admission and discharge documentation, or patients who feel left in the dark between rounds. Priorities vary too, from easing the workload on a short-staffed nursing team to improving patient experience scores, reducing length of stay or preparing to adopt AI tools as they mature. Clinical teams know those gaps best, so they should help shape the strategy from the start rather than react to a finished design. 

Still, every smart room strategy depends on the same foundation: a virtual care platform that connects it all in one place, rather than juggling disconnected point solutions. This is because a smart room isn’t defined by any single device or application. It’s defined by how technologies work together to improve care delivery. Get the strategy and the platform right, and the smart room can grow with the health system instead of being rebuilt every time its needs change.

“A smart room, to me, is where technology is intentionally integrated to extend the capabilities of the care team… with the intention of coming together to create a cohesiveness and an ease of flow, so that clinicians can take care of patients in the best way possible, removing friction from care delivery, to the point that the technology fades into the background.” 

Dr. Stephanie Lahr, Founder, Vital Thread Advisory, in the ATA webinar From Smart Rooms to Smart Flow 

Key Takeaways

  • A smart room is a strategy, not a device checklist. It should be anchored to outcomes like access, workforce optimization, quality and experience. 
  • Clinical teams should help shape the smart room strategy from the start, not react to a finished design. 
  • The core of a smart room is the virtual care platform that powers it – connecting care teams, clinical workflows, AI-enabled applications, and hospital systems into one seamless experience. 
  • Having an open architecture virtual care platform allows health systems to add new capabilities over time without rebuilding workflows and integrations. 

For a step-by-step approach on how to shape your strategy, download the whitepaper, 5 Lessons for Defining and Executing a Smart Room Strategy. 

Why are smart rooms important now?

Walk into most hospital rooms today and you’ll find more technology than ever: a TV, a whiteboard, a nurse call system, a camera, maybe a tablet or two. What you often won’t find is that technology working together. 

That’s the problem smart rooms are meant to solve. Instead of adding one standalone tool after another, health systems are working toward a more coordinated environment. In that kind of room, technology is connected to the workflows and systems that support care, patients stay informed, and care teams have more ways to reach them. 

The timing reflects real pressure. Health systems face nursing shortages, rising patient acuity, rising costs and growing demand for access. Asking more of stretched care teams isn’t the answer. Extending their reach is. 

The technology meant to help has often added complexity instead. The patient room is crowded with point solutions, and each one brings its own device, integration, support contract and training burden. 

Meanwhile, AI is moving fast. Ambient listening, computer vision and contactless monitoring show real promise for patient safety and caregiver workload. But most hospitals don’t yet have the foundation to use these tools at scale, connected to the EHR and built into the workflows clinicians already use. 

Leaders feel the tension between building for the future and getting through today. As one system chief nurse told AvaSure Chief Clinical Officer Lisbeth Votruba: “Smart hospital investment is the most important thing we need to do for our future. But we have to survive today.” A well-designed smart room strategy addresses both. 

What technology is in a smart room?

Every smart room is configured to the health system’s goals, but many share the same building blocks. At the center is a virtual care platform that provides the audio and video these components rely on. 

Component What it does in the room 
Virtual care platform The foundation. Connects care teams, clinical workflows, devices, and AI-enabled applications in one system. 
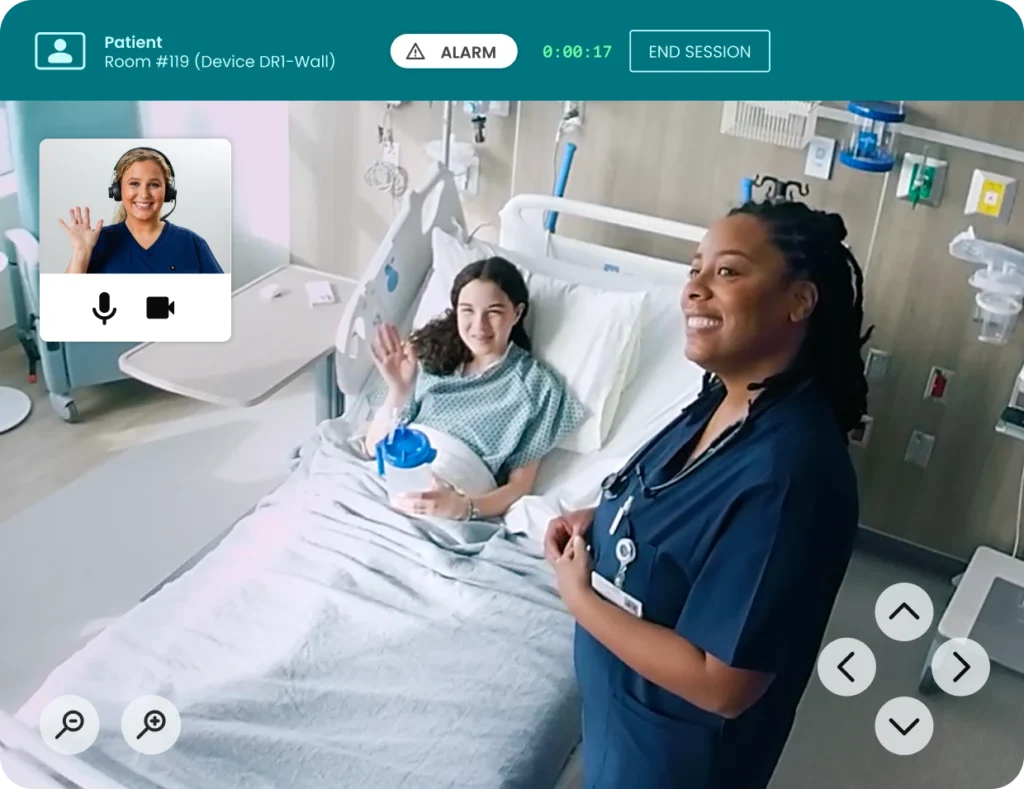
Virtual care services Virtual nursing, virtual visits, and continuous observation, delivered over two-way video and audio. 
Computer vision Use the in-room virtual care device to see and understand what’s happening when staff aren’t in the room – supporting fall, elopement and pressure injury prevention. 
Ambient listening Captures conversations through the in-room virtual care platform so clinicians can care hands-free and spend less time documenting. 
EHR integration Brings labs, history and imaging into the room and keeps virtual care inside existing workflows. 
Room displays The in-room TV, digital whiteboards and door signs share real-time information with patients, families, and staff. 
Connected systems Nurse call, translation services, patient monitoring devices, and other clinical peripherals. 

Without a shared platform, these components become another set of point solutions. With one, care teams and patients are given a consistent presence at the bedside, even when no one is physically there.  

“The smart hospital isn’t defined by one application or one device. It’s defined on how the technology in the room works together in a single platform, so that every time one of those innovates, the room gets smarter… the room becomes an active participant in patients’ care. And we can have safer care, giving caregivers support and health systems the intelligence that they need.”

Lisbeth Votruba, MSN, RN, Chief Clinical Officer, AvaSure, in the ATA webinar From Smart Rooms to Smart Flow 

How can a smart room evolve over time?

Point solutions address a specific need, often on one unit. A smart room platform gives health systems a foundation to support more use cases across care units and care settings and add capabilities as priorities change.  

 Point solutions Smart room platform 
Scope One use case, often one unit Multiple use cases, across units and care settings 
Hardware A new device per application Shared devices and infrastructure 
Integration Rebuilt for each vendor Built once, reused by every new capability 
Clinician experience Multiple logins, workflows and trainings One experience inside existing workflows 
Future innovation Limited to one vendor’s roadmap New AI partners plug into the same foundation 

An open architecture means the platform is built to connect with other vendors’ technology, not just its own. Its audio and video infrastructure is available to outside applications through open APIs, and it integrates with the systems hospitals already rely on, like the EHR and nurse call. A computer vision tool, an ambient listening solution or a new AI application from a third-party partner can use the cameras and microphones already in the room, without adding another device. That gives health systems room to choose the technologies that fit their needs and add them over time, so the room can grow without starting from scratch. 

“I think of smart room software in particular as a chassis whereby you can plug in the tools that you need at any point without altering the foundation you have built, the integrations you have gained, and the patient and provider experience.” 

Emily Warr, MUSC Center for Telehealth, in the HIMSS webinar A Clinical Leader’s Guide to Defining and Executing a Smart Room Strategy 

Interoperability also protects patients. As Warr notes, handoffs are where most mistakes happen, and that is as true for disconnected technology as it is for shift change. 

What results do smart rooms deliver?

Smart rooms improve patient safety, give care teams back time and produce outcomes finance leaders can measure. 

Safer care with the same workforce. Harris Health partnered with AvaSure for virtual sitting to protect patient safety despite resource constraints. 

“We’re not replacing any of our bedside personnel, we’re just taking some of that burden off of expecting them to be all-knowing, all-seeing… I think our nurses have really enjoyed having that piece… They’ve got that extra set of eyes supporting them, and if that observer is recognizing something, like the patient’s beginning to get out of bed, there’s an early intervention, and so we can start to move those pieces more quickly than if that responsibility had been solely on the bedside nurse.” 

Leslie Ferrell, MHA, Administrative Director of Virtual Care, Harris Health, in the ATA webinar From Smart Rooms to Smart Flow 

Better access and fewer readmissions. At Jersey Shore University Medical Center, hospitalists use AvaSure to reach patients in their rooms on demand. 

“We have had the pleasure of working with AvaSure, which lets us be in patients’ rooms on demand when they have questions or need follow-ups… I believe that it not only improves the patient experience and the value we provide, but also prevents readmissions.” 

Dr. Mohamed Bakr, VP, Hospital Medicine, Hackensack Meridian Health, in the ATA webinar From Smart Rooms to Smart Flow 

Measurable financial results. Virtual care programs built with AvaSure have achieved a 65% reduction in RN traveler hours, a 26% reduction in RN overtime, an 11.6% reduction in length of stay and 34 fewer readmissions, tracked year-over-year on the same unit. Virtual sitting replaces an average of 70% of 1:1 sitter spend, and those savings can help fund the rest of the program. 

Financial return isn’t the only measure. Ferrell’s team also tracks observation hours, safety events, escalation time, nursing time and discharge timing. 

“Sometimes we get so focused on what is that financial return, that we forget to pay attention to workforce capacity, patient safety, throughput, access to expertise, staff experience, and patient experience. All of those things matter.” 

Leslie Ferrell, MHA, Administrative Director of Virtual Care, Harris Health, in the ATA webinar From Smart Rooms to Smart Flow 

How do you build a smart room strategy?

Start with the problem, not the technology. In a HIMSS webinar hosted by AvaSure, Emily Warr of the MUSC Center for Telehealth and AvaSure Principal Product Manager Brad Smith outlined how health systems can get it right. Their guidance comes down to five lessons: 

  1. Define the strategy before the technology.  
  1. Design for openness and configurability. 
  1. Bring clinical teams in early. 
  1. Win buy-in by connecting services to outcomes. 
  1. Let your primary objective determine who leads.

“It’s not about the setup in the room, it’s about the service. It’s about solving the problems, it’s about aligning with the strategic priorities of the organization. Once you have those elements in place, that’s when you can choose the technology.” 

Emily Warr, MUSC Center for Telehealth, in the HIMSS webinar A Clinical Leader’s Guide to Defining and Executing a Smart Room Strategy 

The operating model matters as much as the technology. As Leslie Ferrell of Harris Health put it, deployments that struggle usually do so because teams “underestimated the operating model that we needed to have around it,” not because the technology failed. 

That’s why the right partner matters. Look for experience with complex, multi-department implementations, deep clinical expertise to drive change management and adoption, and a customer success team that stays with you long after go-live. 

Go deeper: Download the whitepaper: 5 Lessons for Defining and Executing a Smart Room Strategy 

Build your smart room strategy with AvaSure

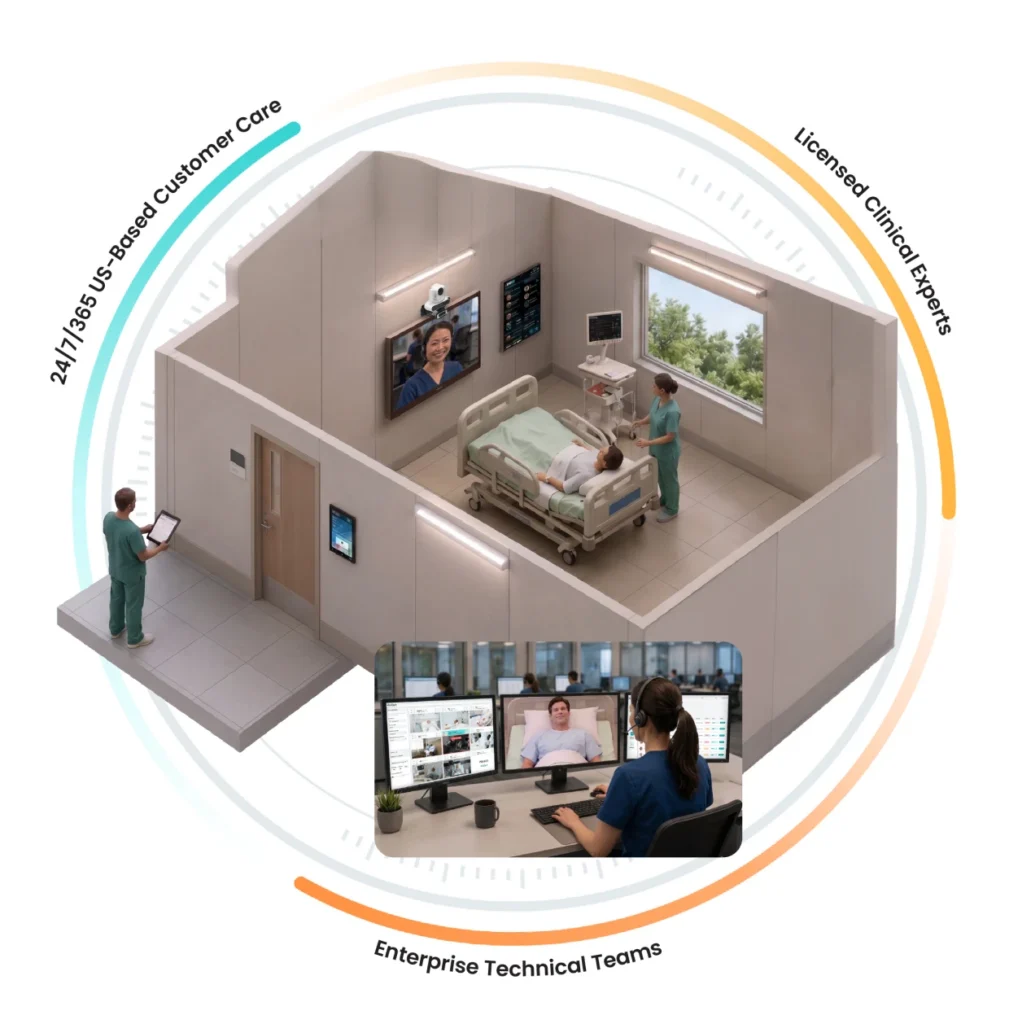
The smart room era is here, and the health systems that start building now will be best positioned for what comes next. AvaSure brings 15+ years of clinical expertise in virtual care, 1,200+ hospital customers and an open platform that connects your EHR, devices, and AI partners. Our clinical team works alongside your nurses and leaders before, during, and long after go-live. 

Whether you’re starting your smart room journey or resetting it, we’ll help you map the strategy to the outcomes that matter most. 

Smart Room FAQ

A smart hospital room is a patient room where virtual care, AI-enabled tools, displays and clinical systems work together on one platform to support patients, caregivers, and hospital operations.

A smart room is the connected patient room. A smart hospital extends that approach across the facility, using connected rooms to improve patient flow and relieve bottlenecks in the ICU, floors and emergency department.

Every smart room is configured to the health system’s goals, but many share the same building blocks. Most include a virtual care platform that provides two-way video and audio, computer vision, ambient listening, EHR integration, in-room displays such as TVs and digital whiteboards, and connections to nurse call, translation services, and clinical devices. 

No. A smart room extends the reach of care teams. Virtual observers and virtual nurses take on tasks that don’t require hands at the bedside so clinicians can practice at the top of their license.

Open architecture lets health systems add new AI partners and capabilities without replacing devices, rebuilding integrations or retraining staff. Each new partner makes the room smarter.

Start with one unit and one problem tied to a strategic objective, such as patient safety, access, or workforce. Bring clinicians in early, then choose technology that fits the strategy.

AvaSure is the virtual care platform powering the smart room. It provides the eyes and ears in every patient room and connects care teams, clinical workflows, the EHR, devices, and AI-enabled applications on one platform.
What is TeleSitter? – How Hospitals Use Virtual Sitting

Use Cases, Benefits, and Considerations for Hospitals

What is TeleSitter? 

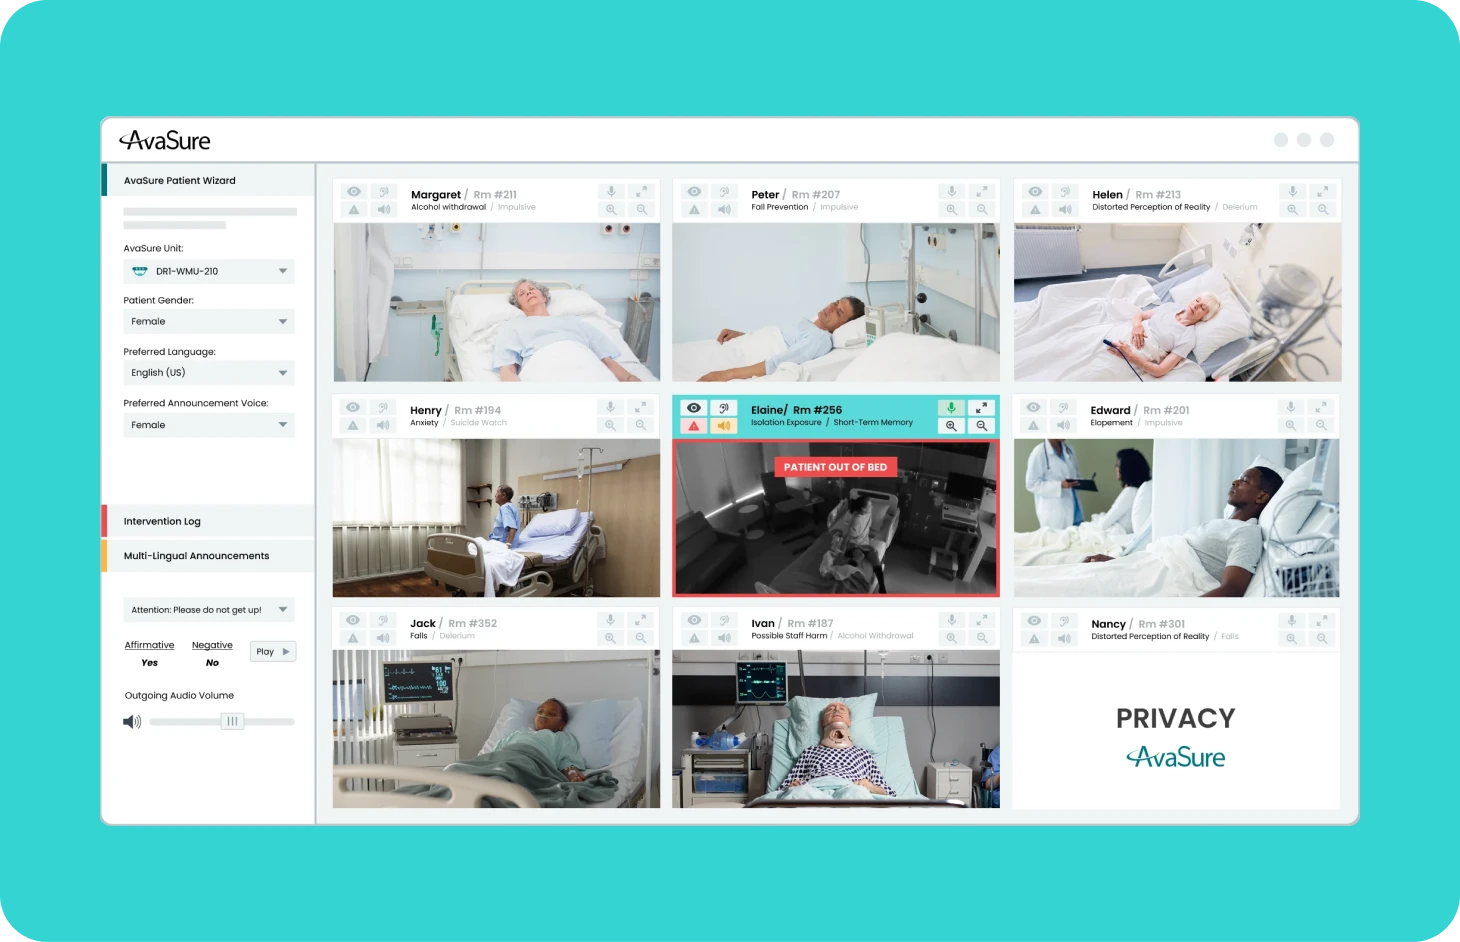
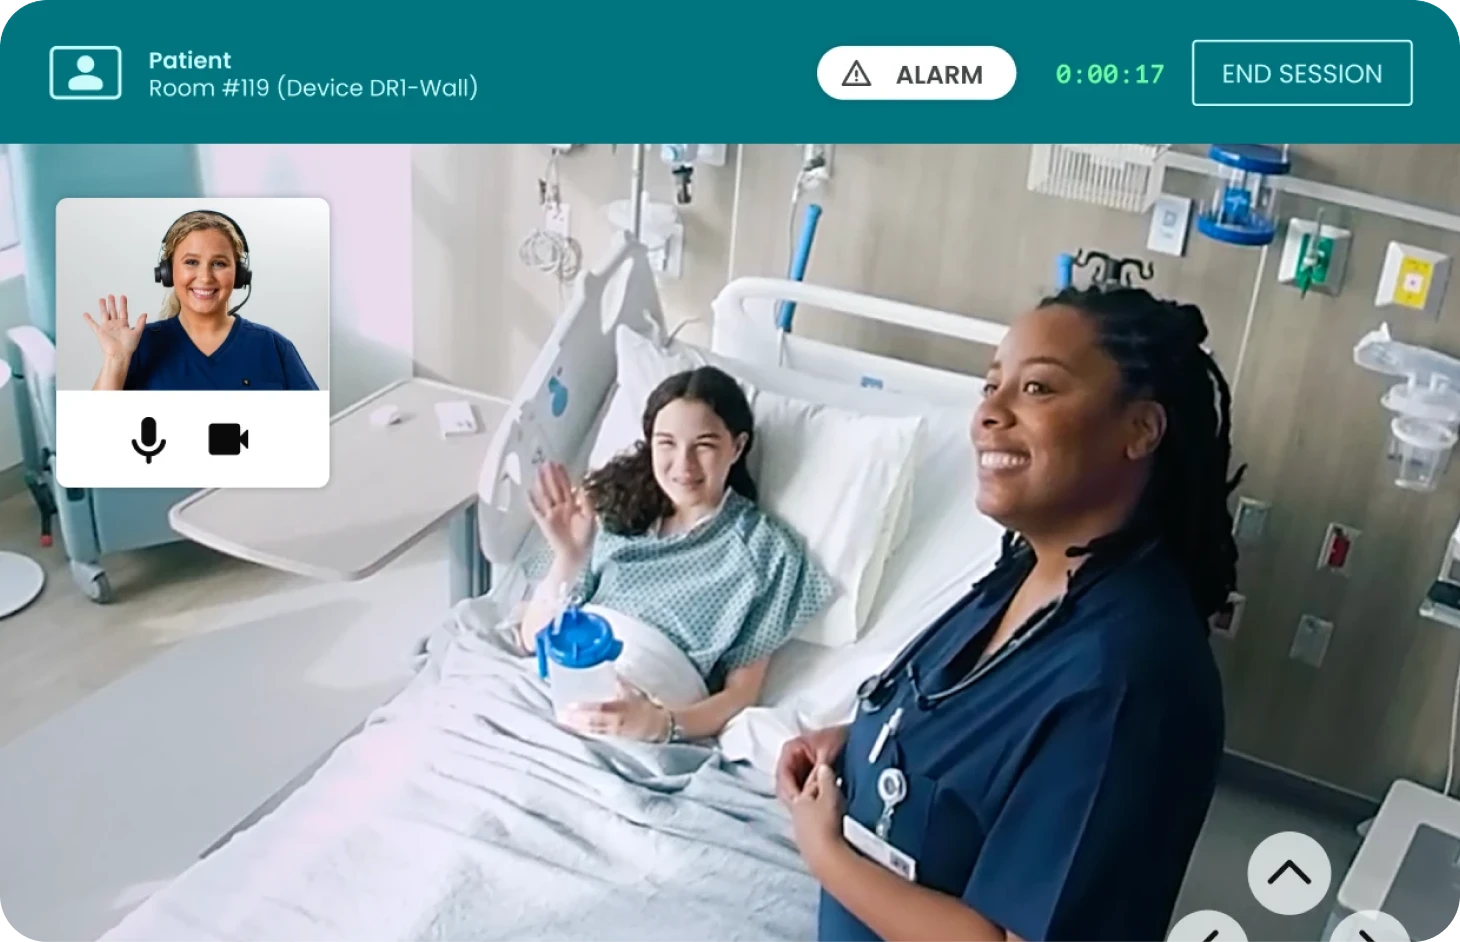
TeleSitter is a continuous remote patient monitoring platform used in hospitals that allows a single trained virtual safety attendant (VSA) to monitor multiple at-risk patients simultaneously. The VSA uses the solution to prevent patient falls and elopement, workplace violence, and behavioral health risks.  

AvaSure invented the TeleSitter® solution in 2008, creating a category-defining remote patient observation technology designed to help hospitals reduce the cost and dependency of one-to-one bedside sitters while maintaining patient safety. The TeleSitter solution delivers a 6x ROI, reduces adverse events by over 50%, reduces reliance on 1:1 sitters by up to 90%, and brings nursing staff back to the bedside.

What does TeleSitter do?

TeleSitter enables a single virtual safety attendant to monitor multiple at-risk patients simultaneously on one screen to prevent falls, elopement, workplace violence, and behavioral health risks. 

Common use cases for virtual sitting:

Fall Prevention

One of the most common use cases for TeleSitter is fall prevention. Virtual Safety Attendants use the TeleSitter application to monitor patients at risk of falls. If they see a patient getting out of bed or not listening to instructions, they can send automated voice commands, speak directly to the patient, or activate the stat alarm — a loud, audible alarm in the patient’s room — to alert bedside care team members that a patient needs immediate assistance. This alarm can be routed through nurse call, mobile devices, or dome light systems for immediate action. Hospitals using TeleSitter have documented fall rate reductions exceeding 50%, and one health system saved $3.2 million from sitter cost reductions and avoided fall-related costs, while another saved $1.5M in just one year. However, while keeping patients safe from falls is where this technology started, it’s only the beginning of what it can do. 

Elopement Prevention

Elopement prevention is another one of the most common use cases of TeleSitter. Patients who are disoriented, cognitively impaired, or in a behavioral health crisis can move quickly, and by the time a bedside nurse notices something is wrong, precious time has already been lost. Virtual Safety Attendants and AI monitoring are trained to recognize the early behavioral cues that precede an elopement attempt — restlessness, repositioning, reaching for side rails — and intervene verbally before a patient ever gets to the door.

Workplace Violence Prevention

TeleSitter can also be used to prevent workplace violence. Healthcare workers face a disproportionately high risk of violence compared to workers in other industries, and placing a 1:1 sitter physically in the room of an agitated patient doesn’t always make that situation safer. Virtual monitoring allows staff to observe, de-escalate, and call for backup from a position that keeps everyone protected. For behavioral health patients more broadly, the ability to maintain a constant, calm, remote presence — one that can redirect without escalating — has proven to be a genuinely different kind of intervention than what a physical sitter can offer. 

Low-to-Moderate Suicide Risk Monitoring

Suicide risk monitoring for patients assessed at low-to-moderate suicide risk is another use case for TeleSitter that has grown substantially and carries meaningful clinical backing. The Joint Commission has formally recognized video monitoring as an acceptable intervention for this patient group, which has given hospitals the confidence to deploy it more broadly across medical and emergency department settings. Research led by David Kroll, MD, of Brigham & Women’s Hospital in Boston, has shown that having a nursing assistant sitting in the room of a suicidal ideation patient is unproven in preventing self-harm. By contrast, use of the TeleSitter solution (now Continuous Observation) on suicide risk patients resulted in zero adverse events (Kroll, 2019). This initial study laid the foundation for The Joint Commission to deem virtual sitting an acceptable intervention for low and moderately suicidal patients.

Pediatric Patient Monitoring

TeleSitter can be used for pediatric patient monitoring through multiple use cases. Pediatric care presents its own unique set of scenarios — from adolescents hospitalized for eating disorders, where constant supervision during meals and bathroom visits is clinically necessary but enormously staff-intensive, to infants at risk of falls when exhausted parents doze off while holding them, to children with autism or developmental disabilities who require consistent, attentive oversight without the potential agitation that a stranger in the room can sometimes cause. In each of these cases, virtual sitting offers a way to maintain the standard of care without the staffing burden that would otherwise make it unsustainable. 

Whether the goal is protecting a vulnerable patient, de-escalating a difficult situation, or giving an overstretched nursing team a little more capacity, virtual sitting has proven it belongs at the center of a modern patient safety strategy.

Benefits and limitations of TeleSitter

The benefits of virtual sitting are real and well-documented. The most straightforward case for virtual sitting is economic: replacing 1:1 bedside sitters with a model where a single Virtual Safety Attendant monitors up to 36 patients simultaneously dramatically changes the labor math. Decades of peer-reviewed research have established that virtual monitoring is not merely equivalent to in-person sitting — in several key areas, it has proven superior. For fall prevention, for suicide risk monitoring, and for workplace violence prevention, studies consistently show that the virtual model performs as well or better than traditional 1:1 observation, while also reducing the emotional and physical burden on nursing teams (The Evidence-Based Case for a Virtual Care Solution). Research published in the Western Journal of Nursing Research found that virtual sitting actively reduces nurse burnout, with bedside staff viewing virtual monitoring as a resource that supports them rather than adding to their workload. That’s a benefit that extends well beyond the patients being monitored. 

One of the limitations of TeleSitter on its own is that it is inherently reactive and scope-limited. While TeleSitter focuses on surveillance and verbal intervention, it does little to address the broader staffing crisis, documentation burden, or clinical complexity driving nurse burnout and attrition. With burnout affecting 56% of the nursing workforce, health systems need more than a safety tool — they need a new model of care delivery.  

That evolution is Virtual Nursing, which extends the same trusted in-room device beyond observation to support admissions, discharges, medication reconciliation, patient and family education, rounding, specialty consults, and novice nurse mentorship — all without switching platforms or disrupting existing workflows. Rather than simply watching patients, Virtual Nurses now actively offload documentation burden, close the experience gap created by staffing shortages, and help systems achieve measurable clinical and financial ROI.

How TeleSitter solutions have evolved

Virtual care has expanded far beyond just virtual sitting. Thousands of health systems around the US have adopted full virtual care programs, where virtual sitting, virtual nursing, and AI workflows come together on one singular platform to streamline clinical workflows and enhance nurse and patient safety. 

AvaSure has evolved far beyond its origins as the TeleSitter solution to become a comprehensive, AI-augmented Intelligent Virtual Care Platform trusted by more than 1,200 hospitals. The solution originally known as TeleSitter® is now called Continuous Observation, a name that better captures the platform’s modern capabilities: a single Virtual Safety Attendant monitoring up to 36 patients simultaneously, supported by ambient AI that detects potential adverse events before they occur. What began as a tool for remote patient safety monitoring has expanded into a unified platform supporting virtual sitting, virtual nursing, episodic consults, specialty care, and ambient AI — all running concurrently on a single in-room device. The Guardian DualFlex exemplifies this evolution: its dual-camera design pairs a 30x optical zoom PTZ camera for clinical workflows with a dedicated fixed wide-angle camera for AI, ensuring uninterrupted computer vision even during active patient consults. Five integrated microphones support ambient listening, voice command workflows, and future AI audio applications — all from one device mounted to the TV, wall, or ceiling. AvaSure’s open Partner API further extends the platform’s reach, enabling approved third-party ambient AI applications (such as Suki and Abridge for clinical documentation) to access device audio securely and write structured notes back to Epic1 flowsheets, without manual entry. AvaSure proudly holds Epic’s Inpatient Virtual Care Toolbox designation.  

AvaSure continues to build the smart room of the future through purpose-built devices, an expanding AI platform developed, and deep EHR integration that makes virtual care a seamless, intelligent part of every patient interaction.

Contact AvaSure to learn more about how our virtual care platform can help keep both your patients and nurses safe.

Key Takeaways

  • AvaSure invented the TeleSitter® solution in 2008, and it has since evolved to what is known today as Continuous Observation. 
  • The most common use cases for virtual sitting are fall prevention, elopement prevention, behavioral health monitoring, low to moderate suicide risk, workplace violence prevention, pediatric safety, isolation/infection prevention, pre-surgical monitoring and seizure monitoring. 
  • The TeleSitter® solution delivers a 6x ROI, reduces adverse events by over 50%, and reduces reliance on 1:1 bedside sitters by over 75% — returning nursing staff to the bedside and alleviating burnout. 
  • Hospitals using TeleSitter (now Continuous Observation) have documented fall rate reductions exceeding 50%, with one health system saving $3.2 million in sitter costs and avoided fall-related expenses, and another saving $1.5 million in a single year. 
  • Peer-reviewed research consistently shows that virtual monitoring performs as well as — or better than — traditional 1:1 observation for fall prevention, suicide risk monitoring, and workplace violence prevention, while also reducing emotional and physical burden on nursing teams. 
  • AvaSure has expanded well beyond its TeleSitter origins, evolving into a comprehensive Intelligent Virtual Care Platform deployed across more than 1,200 hospitals, supporting Continuous Observation, virtual nursing, episodic consults, specialty care, and ambient AI — all on a single platform.

Sources

Kroll, 2019. The Joint Commission. Ligature and/or Suicide Risk Reduction – Video Monitoring of Patients at High Risk for Suicide. 

1Epic is a registered trademark of Epic Systems Corporation.

Nurses Week: How Supporting Nurse Wellbeing Starts with Safer Care Environments 

More than half of U.S. nurses report burnout and ongoing mental health challenges — impacting both caregiver wellbeing and patient outcomes. 

National Nurses Week and Mental Health Awareness Month share the same calendar for good reason. The people we trust most with our lives are facing a crisis of their own. More than half of U.S. nurses report burnout and mental health challenges, impacting both caregiver wellbeing and patient outcomes. Burnout affects up to 56% of the nursing workforce, driven by high stress, chronic understaffing, and administrative burden. In recent years, there has been an influx of nurse walkouts and strikes. In January 2026, roughly 15,000 nurses in New York walked off the job in what became the largest nurse strike in the state’s history—a breaking point fueled by dangerous understaffing, rising workplace violence, and unsustainable workloads.” This moment presents an important opportunity to better support nurses and strengthen the care they provide every day. 

When nurses are overwhelmed, everyone feels it. Patient safety suffers. Staff turnover climbs. And the cycle only deepens. Our nurses give 12+ hours a day to caring for others — but who is caring for them? They are some of the most resilient people in any room, but resilience has its limits. Protecting the people who protect us is essential to the wellbeing of patients and staff alike. Among the many steps that can be taken, the most direct path forward is creating safer, more supportive care environments to support nurse wellbeing. 

The American Nurses Association (ANA) is leading that charge, advocating for mental health resources, workforce sustainability, and the recognition nurses have long deserved. This Nurses Week, join the movement: download the ANA Nurses Week social toolkit to celebrate and honor the nurses who show up for all of us, every single day. 

Technology That Supports Nurses — Not Adds to Their Burden

One way to create safer and more supportive environments for nurses is through virtual care, which plays a key role in reducing cognitive load and administrative tasks, improving staffing flexibility, and creating safer, calmer environments that support mental wellbeing. Improving nurse satisfaction and retention is the #1 reason health systems implement virtual nursing. 

Virtual nursing is reshaping how care teams work, both at the bedside and beyond. Through virtual platforms, nurses and care managers can support bedside teams in real time, helping to educate patients, streamline admissions and discharge paperwork, and automate documentation. This direct, uninterrupted access to patients reduces errors and gaps in the medical record, while freeing floor nurses to focus on what matters most: hands-on patient care. The result is a smarter, more intentional care model — one where RNs, CNAs, and virtual nurses each contribute based on their unique skills and experience, ensuring every patient interaction is handled by the right person at the right time. Beyond the bedside, virtual nursing tools also bridge the gap between hospital staff and external care providers, enabling real-time collaboration that streamlines care transitions and prevents delays in securing post-discharge services. 

Caring Out Loud: A Chief Clinical Officer’s Vision for Supporting Nurses 

AvaSure’s Chief Clinical Officer, Lisbeth Votruba, MSN, RN, FAONL, CAVRN, joined This Week Health’s Nurses Week podcast to talk about what nursing needs most right now and how technology makes it possible. 

A trained nurse practitioner and third generation nurse whose entrepreneurial spirit led her to AvaSure 14 years ago, Lisbeth champions the idea of getting back to old-fashioned, hands-on nursing care and sees ambient listening as one of the most direct paths to get there. Ambient listening is an AI-driven tool that works quietly in the background and can act as a workplace safety tool. If a nurse is feeling in danger, they can simply speak a wake word to trigger an alarm and get help. 

Additionally, ambient listening allows nurses to go hands-free while documenting and give their full attention to the patient — no big computer monitor in the way. Lisbeth introduced this concept as “caring out loud”: verbalizing documentation in real time to keep patients connected to their care while shining a light on everything nurses do. It is important to note that when it comes to documentation, nursing workflows can be more complex than physician workflows as they have less of a natural narrative structure. This is why Lisbeth emphasizes that this technology must be built around the nurse so that they do not have to change the way they interact with patients in order for the AI to document the correct takeaways:

“We want to make sure that the tools are trained to serve the nurses, not the nurses having to be trained to serve the tool.”  

– Lisbeth Votruba, MSN, RN, FAONL, CAVRN, Chief Clinical Officer at AvaSure

As Chief Clinical Officer at AvaSure, Lisbeth ensures nurses have a seat at the table, bringing the clinical lens necessary to redefine workflows and shape the future of care delivery. 

Virtual Care’s Real-World Effect on Nurses 

Virtual Care has been supporting nurses across the US, and there are results to prove it. Through scaling their virtual nursing program, Hackensack Meridian Health (HMH) saw outstanding results that directly benefitted their RNs: 

  • 26% reduction in RN overtime 
  • 65% reduction in RN traveler hours 
  • 9% decrease in documentation time for bedside staff 
  • 12% reduction in length of stay 

As their virtual care journey continues, HMH continues to create an improved environment for nurses, and saw a 28% decrease in RN turnover in the first seven months of their recent care units to go live with virtual nursing. 

Results like these prove how virtual care eases the workload on nurses, creating a healthier work environment for clinical staff, a better experience for patients, and a more efficient health system overall.

Empowering the Next Generation of Nurses 

Virtual nursing isn’t just transforming how we care for patients today; it’s helping to build the nursing workforce of tomorrow. New nurses entering the workforce are already under strain. Virtual nurses serve as an always-available resource for recent graduates and novice nurses — offering real-time mentorship, immediate feedback, and helping new clinicians grow. As virtual care becomes more integrated into hospital workflows and standard care delivery models, it is essential to prepare the next generation of nurses to thrive in this environment. This can include embedding virtual care training into new nurse onboarding and strengthening collaboration between academia and healthcare organizations to support smoother transitions from education to practice.

How AvaSure Cares for Nurses

Nurses are the backbone of healthcare, and for over 18 years, AvaSure has provided them with tools to protect, support, and empower their work. Our intelligent virtual care platform enables virtual care in a diverse range of settings and use cases, with advanced AI, flexible devices, a vast partner ecosystem, real-time insights, and world-class service and support team to guide you every step of your virtual care journey. 

AvaSure is committed to clinical partnership, not just technology delivery. Our clinical team is built by nurses, for nurses — and that foundation shapes everything from how the platform is designed to how it is deployed and supported. Our Clinical Implementation team is 100% nurses who maintain active RN licenses, and along with Chief Clinical Officer Lisbeth Votruba, MSN, RN, FAONL, CAVRN, and AvaSure’s Chief Nursing Executive Advisory Board, they lead the clinical vision behind AvaSure. Because AvaSure’s clinical experts have lived the realities of nursing, they are uniquely positioned to design virtual care solutions that reduce burnout rather than add to it. The result is a platform that nurses can embrace and trust. 

How to Support Nurses Every Day

National Nurses Week is once a year, but nurses deserve recognition every day. There is nothing more important than protecting those that care for us and consistently showing them our appreciation. AvaSure knows that building safer, healthier environments for nurses is an ongoing collaborative effort, and we are dedicated to making that commitment. From innovative monitoring solutions that reduce the physical and emotional burden on nursing staff, to fostering a culture where nurses feel seen, supported, and valued, AvaSure stands alongside the nursing community not just during National Nurses Week, but through every long shift, every difficult moment, and every triumph in between.

Contact us to see how AvaSure can start supporting your nursing team today.

See how smart room technology is continuing to improve nurse safety, mental health, & job satisfaction.

Common Questions

Virtual nursing is the use of virtual care and advanced AI to assist bedside nurses and hospital staff by automating daily clinical workflows like administrative tasks, intake, rounding, admission & discharge, and more. The American Nursing Association describes virtual nursing as a resource that “support(s) the team at the bedside to alleviate the workload and provide greater satisfaction for both the patients and the nursing staff.” 

Nurse burnouts are caused by a number of factors, mainly including chronic understaffing, time-consuming administrative tasks, heavy workloads, workplace violence, long hours, and emotional fatigue. Burnout affects up to 56% of the nursing workforce. 

Creating safer and more supportive environments and listening to nurses’ needs is one of the best ways to prevent nurse burnout. Virtual care helps to prevent nurse burnout by reducing cognitive load and administrative tasks, improving staffing flexibility, and creating safer, calmer environments that support mental wellbeing. 

Through virtual nursing, nurses and care managers can support teams at the bedside to educate patients, complete admissions and discharge paperwork, automate documentation, and mentor more novice nurses. This allows virtual nurses to have direct, uninterrupted time with patients, leading to less errors or gaps in documentation and freeing up floor nurses to care for their patients at the bedside. This also ensures smoother transitions and shorter delays of care for patients. 

Virtual nursing helps with staffing shortages because it allows nurses to return to the bedside and focus on direct patient care, which reduces burnout, increases efficiency in managing workloads, and helps patients receive care more quickly. 

Virtual care tools can reduce workload, improve communication, and enhance patient monitoring—helping nurses focus on high-value care while minimizing stress and burnout. 

Organizations can invest in supportive technologies, prioritize safe staffing levels, provide mental health resources, and create environments where nurses feel heard and supported. 

National Nurses Week, observed each year from May 6–12, recognizes the vital contributions of nurses across the country. It’s also an important moment to spotlight the challenges they face and the need for meaningful support. 

The Rural Health Transformation Program (RHTP): How Virtual Care Can Benefit Rural Hospitals 

Key Takeaways:

  • The Rural Health Transformation Program (RHTP) provides $50B in CMS funding (2026–2030) to strengthen rural hospitals. 
  • States submitted transformation plans prioritizing technology, workforce resilience, and AI. 
  • Virtual nursing, TeleHealth, and tele-specialty consults directly align with RHTP goals. 
  • Hospitals can use RHTP funds to reduce falls, overtime, sitter costs, and specialty care gaps. 
  • Sustainable virtual care models reinvest efficiency savings beyond federal funding. 

What is the Rural Health Transformation Program (RHTP)?

Rural and community hospitals face critical workforce shortages and financial distress, with nearly half operating at a loss as of 2023, according to an AHA analysis of RAND Hospital Cost data. To address these pressures and improve care quality, Congress established the Rural Health Transformation Program (RHTP) under the 2025 One Big Beautiful Bill Act (OBBBA). This $50 billion Centers for Medicare & Medicaid Services (CMS) initiative (FY 2026–2030) provides $10 billion annually to strengthen rural healthcare and offset projected funding gaps. 

How CMS Administers RHTP Funding

States are the direct recipients and had to submit a Rural Health Transformation Plan for CMS approval. Half of the funding is divided equally among participating states—guaranteeing at least $100 million per year for five years if all states join—while the other half is distributed via a CMS formula. This massive pool supports infrastructure, technology, and workforce improvements for nearly 1,800 rural hospitals and 60 million residents.

How Critical Access Hospitals (CAHs) Benefit from RHTP Funding 

While all rural providers are eligible, the nation’s 1,350 Critical Access Hospitals (CAHs) stand to benefit most, particularly in the Midwest and states like Texas, Iowa, and Kansas. By investing in these hospitals, the RHTP aims to prevent closures, preserve essential services like emergency and maternity care, and improve health outcomes in rural America.

How can telehealth and virtual care benefit rural hospitals? 

RHTP applications from numerous states have revealed a priority among rural hospitals: the use of telehealth and virtual care to help extend and improve care where things like specialty care are often unavailable.

virtual nurse checking in on patient and bedside nurse

By integrating telehealth, rural facilities can bridge the “specialty gap,” allowing local doctors to consult with world-class neurologists or cardiologists in real-time without transferring the patient. This “keep it local” approach not only improves patient outcomes during emergencies but also stabilizes the hospital’s finances by retaining admissions and reducing the reliance on expensive traveling staff. In addition, by leveraging AI and virtual care, rural hospitals can expand local access and boost financial sustainability while delivering higher-quality care. These innovations do more than just improve patient outcomes and ROI; they actively reduce safety risks like falls, alleviate staff burnout, and foster collaborative models of care. See how Hackensack Meridian Health improved nurse satisfaction and patient outcomes through virtual nursing. 

How do states plan to use their funding for the Rural Health Transformation Program (RHTP)? 

States submitted plans in December 2025 that had to meet specific criteria defined by CMS. Funding for these plans was released in January 2026. The plans had to address how hospitals will: 

  • Prioritize the use of new and emerging technologies including AI to improve rural health outcomes 
  • Improve access to care locally 
  • Enhance quality metrics for rural patients 
  • Foster partnerships (e.g. small hospitals collaborating with larger systems) and ensure financial stability of rural providers 
  • Tackle causes of rural hospital closure 

How can hospitals leverage RHTP funding? 

1. Engage State RHTP Leadership 

Coordinate with your state health department or Medicaid agency to include virtual care in your Rural Health Transformation Plan. Highlight its impact on workforce resilience and patient safety. 

2. Develop a Turnkey Proposal with AvaSure 

Work with AvaSure to submit a fundable plan covering: 

  • Platform deployment and configuration 
  • Clinical and operational workflow redesign 
  • Staff training and ongoing support 
  • Continuous performance measurement 

3. Measure and Report Outcomes 
 
To strengthen your case, align the stated goals to the RHTP program and track them. The outcomes that AvaSure has benchmarked with partner hospitals with virtual care programs are:  

  • 72% improvement in 1:1 sitter usage 
  • 11.6% improvement in length of stay 
  • 26% improvement in RN overtime 
  • 30-50% improvement in falls  

4. Build a Sustainable Model 

Reinvest efficiency savings and improved performance outcomes to sustain virtual nursing operations post-RHTP funding. 

AvaSure’s maturity model provides a strategic roadmap for health systems to transition from initial pilots to a fully integrated virtual care delivery system. It serves as a vital framework for leaders to benchmark their current capabilities and identify the specific infrastructure and workflow milestones required to reinvest efficiency savings and sustain high-performance virtual nursing long after the conclusion of RHTP funding. 

avasure's maturity model

How AvaSure Aligns with the Rural Health Transformation Program 

AvaSure, the industry leader in virtual nursing and continuous patient monitoring, helps hospitals extend nursing capacity, reduce falls and sitter costs, and enhance care quality through a proven operational model. AvaSure’s virtual care platform is fully aligned with RHTP’s focus on technology-enabled workforce transformation.  
 
RHTP Funding Categories Supported by AvaSure: 

  • Workforce development and modernization 
  • Technology-enabled patient care and safety 
  • Training and technical assistance 
  • Quality and efficiency improvement initiatives 

The Rural Health Transformation Program prioritizes initiatives that stabilize and modernize the healthcare workforce, improve patient safety, and enable sustainable operations in rural hospitals. AvaSure supports all three objectives by bringing virtual nursing and continuous observation into daily hospital operations: 

  1. Virtual Nursing: Augments bedside teams with remote nurses who handle admissions, discharges, and patient education to reduce admin burden. 
  2. Continuous Observation (TeleSitting): Centralized video observation reduces falls, elopements, and 1:1 sitter costs. 
  3. Specialty Consults: Consult with specialists in another location to expand care without having to move your patient.  

This in turn leads to benefits such as:  

  • Workforce Flexibility: Reduces overtime, improves staff retention, and increases productivity.
  • Patient Safety: Delivers continuous monitoring and rapid response support. 

Ultimately, access to care and physician specialists remains one of the most pressing challenges for rural hospitals, leading many to prioritize specialty health and telehealth consults in their strategic applications. To effectively remedy these gaps, it is essential to select a virtual care platform that leverages the specific partnerships necessary to bridge the distance between patients and specialized expertise.

How Can AvaSure Help?

AvaSure’s partnership with Equum Medical, a telehealth-enabled clinical workforce organization, will provide rural hospitals with easy access to virtual specialty consults. The company’s broad portfolio of services addresses the driving challenges of Access and Capacity for health systems, including multi-specialty telemedicine, critical care, virtual nursing, virtual sitter monitoring, and telemetry. Solutions include:  

  • Inpatient tele-specialty consults (e.g., neurology/stroke, psychiatry, cardiology, nephrology, infectious disease, pulmonology, and more) 
  • Tele-ICU and critical care support, including surge capacity and after-hours coverage 
  • Virtual hospitalist support for nights, weekends, and hard-to-staff locations 
  • Care coordination that helps reduce avoidable transfers, keep patients local, and support patient flow with integrated virtual nursing capabilities across care venues 

These solutions strengthen financial sustainability while offering scalable, broadband-friendly technology specifically designed for the unique constraints of rural settings. Unlike typical telehealth partnerships that add separate point solutions, the integrated model runs on a single platform that many hospitals already use for virtual nursing and patient observation, paired with Equum’s physician and clinical programs. 

Your RHTP Virtual Care Strategy 

AvaSure equips rural hospitals with innovative virtual care and AI-powered solutions that expand local access, enhance care quality, and strengthen financial sustainability. By reducing adverse events like patient falls, easing workforce burdens, and fostering collaborative models of care, AvaSure helps rural providers meet and exceed the goals of the Rural Hospital Transformation Program.

Schedule a strategy consultation with AvaSure to explore how RHTP funding can support your virtual care roadmap. 

How AvaSure Builds AI for Patient Safety

Hospitals are under pressure to reduce preventable harm from falls, elopement, and other adverse events while maintaining a sustainable workload for clinicians. Camera-based monitoring and virtual sitting programs such as AvaSure’s Continuous Observation platform have already demonstrated that continuous observation can reduce falls and injuries, but human-only monitoring does not scale indefinitely. Many organizations are now exploring Artificial Intelligence to extend the reach of their teams, and to detect risk earlier than a human observer might be able to do consistently. 

At AvaSure, we view Artificial Intelligence as an extension of the virtual care platform that more than 1,200 hospitals already use for continuous observation, virtual nursing, and specialty consults. Our goal is not to replace human judgement. Instead, we want to build behavior-aware monitoring that can recognize patterns associated with risk, surface those patterns to caregivers in time to intervene, and do so in a way that is technically sound, clinically grounded, and respectful of patient privacy. 

This blog describes the design principles behind our Falls and Elopement Artificial Intelligence system. AvaSure leverages Computer Vision, a subset of Artificial Intelligence, to detect high-risk scenarios before an adverse event occurs. Our Computer Vision models perceive the hospital room environment by learning what situations are unsafe for patients. This allows us to demonstrate the clinical performance of our models made possible by our onboarding process for new hospitals. Built on Oracle Cloud Infrastructure (OCI), this cloud-based system provides a scalable foundation that extends beyond fall and elopement prevention into broader ambient AI applications. 

What are the Challenges of Computer Vision Models for Falls and Elopement?

Falls and elopements rarely occur as single, isolated moments. They emerge over a sequence of behaviors. A patient may shift position in bed, sit upright, move to the edge of the bed, stand, and then begin to move away. However, there are challenges to building Computer Vision models that understand such behavior. Staff and visitors come and go, sometimes obstructing the view of the camera. Lighting changes over the course of the day and night, including the use of infrared lighting in low light situations. All these challenges are part of the design space, and a monitoring system that considers a single video frame at a time without regard to such confounding elements can miss much of this context.  

An important way to adapt to these challenges is to select the right type of camera device. Choosing the right device for AI for patient safety also impacts how the system perceives the hospital room environment. AvaSure offers a variety of camera devices including Guardian Dual Flex, Guardian Mobile Devices, and Guardian Ceiling Devices. Guardian Dual Flex devices provide a fixed camera dedicated to Artificial Intelligence monitoring. Mobile units introduce variation in pan, tilt, zoom, and location within the room – each of which varies in layout across and within different hospital systems. Guardian Ceiling devices provide a different perspective compared to Dual Flex and Mobile devices. 

AvaSure’s Computer Vision system and onboarding processes are built to adapt rather than assuming a single, fixed installation environment. Our current models for Falls and Elopement focus on understanding posture and presence over time while accommodating variations in lighting and environment. The system distinguishes the posture of the patient from lying in bed, sitting on the side of the bed, or standing. These states are evaluated over short time windows and combined with rules that relate them to risk. For example, a transition from lying to sitting on the side of the bed may be treated as an early warning, whereas a transition to standing unassisted may prompt a higher-severity alert. 

How Does Falls and Elopement AI Perceive the Patient Room?

The Falls and Elopement models employ a three-layer approach to perceive conditions within the hospital room. 

  1. Lowest Layer: Detect whether there are people in the frame and estimate how many. 
  1. Middle Layer: When there is a single person in view, form an understanding of posture and location relative to the bed and other furniture. 
  1. Top Layer: Combine these posture estimates over time and apply rules that map temporal patterns to alerts. 

This layered approach is intentional. Computer vision research has shown that models built only around pose estimation can struggle with common conditions in clinical rooms, such as occlusions from blankets and equipment, low light, and cluttered backgrounds. By combining person detection with semantic posture classification and temporal reasoning, we maintain flexibility in camera hardware while capturing clinically meaningful patterns in the room. 

The temporal aspect is central to how the system works. Rather than categorizing each frame in isolation, the models consider short windows of behavior and pay attention to transitions. A single frame showing a patient near the edge of the bed may not be sufficient to decide whether they are attempting to stand or simply shifting position. A sequence of frames that show a consistent movement from reclined to upright to standing is more informative. Alerts are based on this kind of sequence-aware understanding rather than a momentary snapshot. 

AvaSure designs for known sources of variability. Mobile cameras introduce changes in viewpoint and zoom as they are repositioned. Different rooms may be arranged in mirror images, with beds and bathrooms on opposite sides. Lighting can range from bright daytime scenes to low-light conditions at night. During model development and onboarding, we deliberately include these variations so that the system can learn to interpret similar behaviors across a range of visual conditions. 

How does AI for Patient Safety Learn Real-World Clinical Complexity?

Computer Vision models learn by being fed many examples of different situations. For example, these could be labeled as “a patient lying in bed” or “a patient standing near the side of the bed”. The learning (or training) process then iteratively adjusts the model parameters based on how well the model at that iteration correctly predicts the situation associated with a given example. This process repeats until the model performs well enough. There are several methods for capturing data for training, including having actors stage scenes and having computers generate synthetic scenes by rendering life-like situations. 

However, models trained only on staged scenes and synthetic data tend to perform best on those same controlled scenarios. Real hospital rooms are more complex. Patients vary widely in demographic, mobility, and behavior. Equipment is added and removed. Staff and visitors move through the field of view in unpredictable ways. To build models of AI for patient safety that can handle this complexity, we need to learn from images that reflect it. At the same time, patient identity and privacy must be preserved. 

AvaSure maintains a patent-pending patient anonymization system that allows us to incorporate real-world imagery into training and evaluation without retaining identifiable visual information. The system applies transformations that remove or obscure personally identifiable features and present them to a human reviewer. The reviewer confirms that anonymization is complete and assigns labels describing the posture and relevant contextual details. Only after this confirmation do the frames enter curated data sets used for training and for measuring performance in production. 

The system captures frames concentrated around ambiguous or clinically relevant situations rather than random samples of uneventful periods. This makes them particularly useful for improving model performance for video cases where decisions are hardest. 

Precision vs Recall: Which Metrics Matter Most for Clinical Success?

When evaluating models in safety-critical domains, accuracy alone is not sufficient. Falls and elopements are relatively rare events compared with the number of hours of observation across a hospital. A system can achieve high overall accuracy by correctly labelling long periods of low-risk behavior yet still miss important events or generate more alerts than staff can reasonably handle. 

For this reason, AvaSure frames performance in terms that reflect the realities of clinical operations. Precision captures how often an alert corresponds to a meaningful event. Recall captures how often the system detects an event when it occurs. The F1 score combines the two into a single measure that balances false positives and missed detections. These metrics tell us how often the system asks for attention when it is truly warranted and how often it remains silent when it should speak up. 

In practice, different hospitals and units may prefer different trade-offs. A neurosurgical ward may choose to tolerate more alerts in exchange for fewer missed events, whereas a lower-acuity unit may prioritize reducing unnecessary interruptions. Our models can operate at different points along the precision-recall curve, and part of the onboarding process is to discuss and tune that operating point together with clinical and operational leaders. 

Beyond the initial deployment, AvaSure treats performance as something that must be monitored and maintained. As room layouts, staffing patterns, and patient populations change, the distribution of behaviors the system sees will change as well. By sampling outputs in the field for new models running side by side with existing models, we can compare new model versions against established baselines and roll back changes that do not meet defined criteria. 

Deployment Without Disruption: What is the Process for Onboarding New Hospitals with AI for Patient Safety?

For hospitals, the most important questions are how the system will behave in their specific environment and how disruptive deployment will be. AvaSure’s onboarding process is designed to answer those questions incrementally and transparently. 

The work begins with understanding room configurations, typical camera locations, and the kinds of patients and use cases each unit expects to monitor. This can include having AvaSure team members stage representative scenarios in sample rooms, capturing video that reflects local layouts, lighting, and camera angles. This staged data helps verify that the baseline model behaves as expected before any live patient feeds are involved. 

As cameras are connected, we run the models in background mode. The system processes live video, but alerts are not yet sent to staff. During this period, we collect anonymized frames of interest and review the patterns of potential alerts. This is also when we fine-tune the operating point where we can adjust the precision vs recall for the unit’s needs. 

Once the hospital is comfortable with the system’s behavior, alerts are enabled for virtual safety attendants. The user interface will increasingly support structured feedback so that attendants can indicate whether an alert was helpful, spurious, or associated with an event the system should have recognized. These feedback signals, together with anonymized frames, feed back into our data and model improvement process. By gathering room dimensions, lighting, and arrangement details, we are able to use rendered scenes that are specific to each environment, streamlining the creation of training examples for new hospitals. 

How to Extend Beyond AI for Patient Safety Monitoring

Falls and elopements are a natural starting point for behavior-aware monitoring because they are common, clinically important, and directly connected to existing continuous observation workflows. However, the same sensing and inference capabilities can support a broader set of safety and quality use cases over time. 

AvaSure’s AI Augmented Monitoring strategy anticipates an expansion from Falls and Elopement into additional use cases such as hospital-acquired pressure injury prevention, infection-related behaviors, and staff duress. Environmental sensing capabilities, including detection of meal tray delivery and removal or patterns of in-bed movement, can contribute to these use cases by providing objective, continuous signals about patient status and care processes. Each new application will require its own feasibility studies, data collection plans, and validation steps, but they build on the same underlying platform and design approach. 

Each of these additional use cases requires enhancements to the Computer Vision models to have them comprehend a wider variety of situations. Such enhancements can require additional or more complex models requiring additional computing power. AvaSure leverages OCI’s AI infrastructure offerings to bring to bear considerable GPU-powered computing to support an expanding range of use cases. 

How do we integrate security and compliance into the design of healthcare AI models? 

Security for us is not a separate track from Artificial Intelligence; it is part of the design of the platform and the models from the beginning. AvaSure’s virtual care systems already operate in environments where SOC 2 and HIPAA expectations are the baseline, not an add-on, and the same standard applies to AI Augmented Monitoring. Every new service that touches patient data, from model pipelines to anonymization computing, is expected to pass formal design review, threat modelling, and, where appropriate, penetration testing before it is considered ready for production. 

At the infrastructure level, our cloud strategy is built on a scalable, multi-tenant architecture designed to keep different users and services securely separated. Robust identity and access management ensures that only authorized components can communicate or access sensitive data, and every service operates with the minimum permissions required. Data moving through the system is protected by encryption, as is data stored in managed services. Comprehensive audit logging is a core part of our approach, recording authentication and authorization events, configuration updates, model changes, and administrative actions so that security and compliance teams can thoroughly review activity if needed. 

For AI specifically, the same security-by-design approach applies. Security specialists review designs for new AI use cases during ideation rather than waiting for prototypes. The review looks at how video streams enter the system, where inference is performed, what outputs persisted, and how PHI is handled or removed. This helps ensure that the introduction of GPU-backed inference or new data flows does not inadvertently expand the attack surface or weaken isolation guarantees.  

The anonymization pipeline is an example of security and privacy concerns shaping the technical design. Rather than storing raw patient video, the system extracts short windows around events of interest and routes them to a separate anonymization service. That service applies privacy preserving transforms and requires human confirmation that identifiable information has been removed before frames can be used for training or evaluation. All of this traffic is encrypted in transit; anonymized images are encrypted at rest and stored with restricted access. This architecture allows the models to benefit from realistic data while maintaining clear boundaries around PHI. 

In practice, ensuring security involves closely connecting monitoring activities with incident response protocols. A comprehensive strategy includes full observability across systems and processes, using tools like metrics, alerts, dashboards, and health checks to quickly detect and respond to any unusual activity. The same mechanisms that support autoscaling and automated rollback for availability also support security; if a change in configuration or dependency were to introduce unexpected behavior, operators can detect it quickly and revert. Regular risk assessments, combined with continuous integration and deployment practices, are intended to keep the platform aligned with evolving threats and regulatory expectations rather than treating compliance as a static checklist. 

From the hospital’s perspective, the outcome of this approach should be straightforward: AI features sit inside a platform that is already held to enterprise security and compliance standards, and any new capability is expected to meet those standards before it is offered in production. The same controls that protect virtual care today – access control, encryption, audit logging, and formal review – apply equally to behavior-aware monitoring and future AI use cases. 

How Does AvaSure Scale AI for Patient Safety in Modern Health Systems? 

Building AI for patient safety is not simply a matter of choosing a model architecture or training on a large data set. It is a system-level effort that spans model design, data collection, anonymization, infrastructure, onboarding, monitoring, security, and governance. Each part influences how the technology behaves in practice and how much clinicians and patients can rely on it. 

For AvaSure, the core elements of that system are clear. We focus on understanding behavior in context rather than isolated frames. We adopt a stepwise development approach that involves staged experiments, demonstrations, and validation in real clinical settings. We learn from real rooms through an anonymization data collection system that protects identity while concentrating on data where it matters most. We operate on a cloud platform designed for reliability, scalability, and security. Lastly, we treat hospitals as partners in an ongoing improvement process rather than one-time installations. 

AvaSure is building AI for patient safety into the virtual care platform that customers already use for continuous observation and virtual nursing. Future blogs will explore specific components in more depth, including anonymization and data curation, our hybrid edge–cloud roadmap, and the evolution from single-use models to a suite of AI augmented monitoring applications. For now, our aim is to make the underlying approach visible so that hospital leaders and clinicians can make informed decisions about how AI fits into their own patient safety strategies.